Total Pageviews

Translate

Followers

Thursday, July 2, 2015

Accessory Navicular and Tarsal Tunnel: Email Advice

Accessory Navicular Problems: Further info from the initial blog post

Dr. Blake,

I am a 31-year old professional who currently works in an office in Massachusetts. Last year, however, I spent 9 months in Spain teaching English. I had no car and found myself doing lots of walking. I also gained about 15 pounds in the first couple of months there. I noticed after three months of walking in ballet flat style shoes a burning sensation in my right ankle. Long story short, here we are a year and a half later and I still have the pain. I weigh about 125 and am 5'2".
Dr Blake's comment: Tentative diagnosis is Tarsal Tunnel Syndrome. This is neuropathic pain, and needs to be treated with a nerve emphasis, some mechanical changes, and some anti-inflammatory measures.

I have seen a total of four doctors so far. I have done PT, tried custom orthotics (which I lost during my move back), tried a walking boot for 6 weeks, been on a couple strong NSAIDs, modified my activities, and tried ice and heat therapy at home on a sporadic basis.
Dr Blake's comment: This problem is helped with the mechanical support of the orthotic devices, especially if there is some varus wedge at the heel. Also, nerves love heat not ice, motion not lack of motion, no massage, and gentle stretching (like neural gliding). 

The orthotics caused more foot pain in other areas, so I am not sure they were made properly for my condition. The PT was done in Spain a year ago and consisted of 45 minutes of heat therapy, electric wave therapy, and massage every day for three weeks.

Six weeks in the boot this past winter was creating problems in my left knee and hip. They never gave me a leveler for the other side, but I did wear a high shoe which seemed okay.

Please help with your opinion! My current doctor who is an orthopedic surgeon and prescribed the boot is of the persuasion that PT and orthotics will not help the edema he sees on the MRI in my bones. I personally want to try a new PT routine and new orthotics before I resort to surgery, but that means I will have to move on to a new doctor yet again. Two doctors were in Spain and the other was here in the U.S. (podiatrist with a horrible bedside manner who said paying $400 for orthotics from his office was the only option).

I am so frustrated and feel like I have tried everything but I also think the timing and quality of the things I have tried could be reassessed and tried again. What do you think?
I don't want surgery if possible. It is my right foot and it will make me unable to drive.

Dr Blake's comment: Without a history of a fall or collision causing major injury, the need for surgery is typically small. Yes, starting again sounds the best. The bone edema could be residual for a stress fracture that has healed or is still healing, and the inflammation from the bone injury putting pressure on the nerves leading to the burning. Burning is classic nerve pain. You need to create your pain free environment however while you search out a new doctor. Typically sports medicine doctors, not necessarily podiatrists or orthopedists, are the best. If 6 months has passed from the first MRI, get another to assess the amount of healing. You may not feel any better until the bone edema is all healed. It is a reflection of bone trauma. Go back into the boot part of the day if you can not find another environment to keep the foot happy. See if warm water soaking works better than contrast bathes. If your skin can tolerate some massage, order NeuroEze online and massage 3 times per day, at least above and below the sore areas. Also do neural gliding 3 times per day, as long as it is comfortable. If warmth or contrast does not help, stay with ice packs. You can experiment with placing the ice pack over the area, or above it. Send me other info on what you have found works and does not work. Are you better in heels vs flats, barefoot vs shoes, etc? How long can you walk without limping? Send a photo of your foot with your finger pointing to the exact area. Hope this starts the forward progress. What exact diagnoses have you been given? Rich

Hi Dr. Blake,

Thank you so much for responding. I will do my best to answer your questions.
I have an accessory navicular in both feet (see photo of right foot with me pointing to general area of pain). I only realized they existed recently, because they never caused me any pain before, and I only present symptoms in the right foot. The pain changes places; sometimes it is under the arch, and other times there is a shooting pain up the post tibial tendon. Some days it feels like a rubber band about to snap with too much pressure, and other days it's that burning I described. I also have flat feet.
Dr Blake's comment: That definitely sounds more like an accessory navicular problem. Since it involves the posterior tibial tendon in the tarsal tunnel, you can get nerve pain or nerve symptoms being generated. 

It seems like switching shoes often helps. Barefoot is bad. I have spent more money on shoes in the past year than in my entire life! Dr. Scholl's inserts, MBT rocker bottom shoes (horrible for my condition), Clarks, sneakers, really expensive clogs, etc. The clogs (with a raised heel) are my favorite. However, I refuse to wear them in the summer as I still have some sense of fashion to maintain. I just bought some comfortable Clarks to get me through the summer that look like ballet flats but have a much better sole and support, with a wide toe. I'm also in love with Okabashi flip flops, and wear them around the house as much as possible.
Dr Blake's comment: If you can get comfortable, but stable orthotic devices, the design can be used in your sandals with a removable insole. 
http://www.drblakeshealingsole.com/2010/07/orthotic-devices-for-sandals-more.html

The MRI was done in January 2015 and we are now in May. My condition has not changed symptomatically since December 2013. My orthopedist believes that physical therapy will inflame the edema more, or be useless. He is also not a fan of orthotics, which I tend to agree with, because from what I've read online, they don't make your feet work hard enough and allow them to lazily conform to a mold. Some doctors believe they create dependency. What is your view on this?
Dr Blake's comment: I love orthotics for this problem. I believe you only need to do 2-3 minutes a day of strengthening to make up for any weakness from the bracing effect. And strengthening the posterior tibial tendon should be part of your program. You must understand, since you are still trying to get into a pain free environment for most activities, you are still technically in the Immobilization/Anti-Inflammatory Phase of Rehabilitation, so any assistive aid is very appropriate now (especially when some are suggesting surgery). 


https://youtu.be/QP3Ud4d39dc

So you think I should try using the boot again even though it didn't cure the condition in 6 weeks, just for comfort, while I search for a sports medicine doctor? The boot does cause problems in the left hip and knee if I wear it too long, but I will certainly do anything to get better! I will also mention that I am developing a bunionette on the right foot from compensating, as well as from wearing winter boots with a tapered toe. Not too happy about this!
Dr Blake's comment: See the video on Tailor's Bunion care. 
http://www.drblakeshealingsole.com/2013/11/tailors-bunion-you-tube-comment.html

I am currently taking Meloxicam and it doesn't seem to be helping after a month. I was on Indomethacin for a few weeks, and while I believe it did help reduce inflammation temporarily, the side effects were awful. You are correct in stating the foot likes heat better than ice.
Dr Blake's comment: At this stage you have both inflammatory pain and nerve pain. And they can trade off on a daily or weekly basis what gives you the current symptoms. Try to see if you can distinguish the various types of pain, and what treatments help them. 

My life has changed completely and I cannot play tennis, do Zumba classes, or walk long distances anymore. It has affected my social life and career as I must ask co-workers, family and friends to coordinate activity around my pain. Sometimes I push myself when I'm alone because I need to get things done (cleaning, vacuuming, etc). but I suffer the following two days recovering.
Dr Blake's comment: This is why I would err on getting and learning all forms of immobilization: various taping, different orthotic designs, Aircast PTTD brace, removable boots, AFOs, shoes, and power lacing. Read the posts on posterior tibial tendon dysfunction to see all these avenues like the one below.
http://www.drblakeshealingsole.com/2012/11/posterior-tibial-tendon-dysfunction.html


The reason I have hope for recovery is that I have had a couple sporadic days with absolutely no pain. I did not change anything activity-wise, so I have no idea what alleviated the symptoms. I hope I am being reasonable by avoiding surgery. I am very anxious about it, but I also don't want to avoid it forever if it's really the best option. It seems that the body can heal itself in many cases given the right conditions, and want to exhaust all options before going under the knife, being out of work, collecting disability, etc. I am a very active person and while I have rested the foot a great deal, I won't pretend it's been easy to slow down.
I'd like to lose 10 lbs. because I think being a little lighter will alleviate some pressure, but I am not even overweight and don't want to have to maintain a low weight my entire life just for this reason (I.e., what if I get pregnant someday)? I think the weight is a contributing factor, not a root cause. I am having a hard time losing weight with the condition, ironically.
Thank you again for your time, Dr. Blake. I sincerely appreciate it!

Dr Blake's comment: Good luck. Here is my typical checklist for accessory navicular issues (with tendinitis and tarsal tunnel symptoms just part of the overal syndrome).

The top 10 treatments for accessory navicular syndrome:

1.  An MRI is very important to discover what the source of pain actually is: stress fracture, joint inflammation, or tendinitis. There is a joint between the navicular and its accessory bone.
2. Use Kinesio Taping or supportthefoot.com tape or classic low dye taping techniques intially 24/7 and then for extended activities.
3.  Ice pack the sore area 10-15 minutes 3 times daily.
4.  Go into a removable boot (such as an Anklizer) for 2-3 months if needed to calm the foot down.
5.  Strengthen the posterior tibial tendon starting initially with active range of motion like ankle circles.
6.  Check out the Aircast Airlift PTTD brace to see if it is helpful for you and can get you out of the boot faster.
7.  Custom foot orthotics are a must for a 2 year period. They must produce a good force against the navicular, but it may take time finding the right orthotic guy/gal.
8.  You can use Sole OTC orthotic devices with medial longitudinal Hapads initially until a good protective orthotic device is made.
9.  Create a pain free environment as soon as possible (level 0-2).
10.  If the MRI shows bone reaction (edema), order a bone stimulator as soon as possible to start strengthening the bone.

Wednesday, July 1, 2015

Podiatry and Humor make for Great Healing

Please enjoy!!! Rich

Water Brace for Ankle Rehabilitation: Posterior Tibial Tendon Injury

This patient of mine is currently recovering from a posterior tibial tendon injury. Her MRI showed inflammation without tears, so we are moving her along in the rehabilitation process. We had discussed no kicking in the water at this point due to the added stress on the tendon, and definitely no fins of any form.

Hi Rich,

I apologize again for being late this morning, after asking you to
be on time.  Thanks so much for your patience and understanding.

Re: swimming (no fins) being stressful on my ankles

1.  Would this, or something like it, allow me to swim w/out putting
that float thing betw my legs?

2.  Would it work for water aerobics?  Can I go to water aerobics in another month or 2?
   (it does involve some jumping, etc) What if I use one of those wrap-around-your-waist float things and my
    feet don't touch bottom?

3.  Were you saying that I should NEVER swim w/out that float thing?

I made an appt for a month from now.  Hope it's not too much trouble to respond to these ???s.

Thanks again!

Best,

Dr Blake's response after reviewing the link:

Thanks, that looks great. It will help the biofeedback loop telling your brain that you are protected and that you can swim, while you still must avoid excessive kicking in the pool. Still go easy and ice for 15 minutes after swimming whether it hurts or not. Your MRI was too good to have any permanent restriction on activity, but it will take you 6-9 months to get that injured posterior tibial tendon super strong. Yes, you can begin water aerobics in 2 months, just start with brace and no weight bearing for the first month. And we will see how it goes.Hope this goes well. Rich

Saturday, June 20, 2015

Big Toe Joint Pain: Podiatry Today Post

I just got invited to host a monthly blog post for podiatrists in a magazine entitled Podiatry Today. It is another good source of information for podiatrists and lay patients alike. Hope it is helpful. 

http://www.podiatrytoday.com/blogged/addressing-longtime-%E2%80%98big-toe-pain%E2%80%99-younger-active-patient

Correcting Children with Flatfeet with Orthotic Devices

Custom Made Orthotic Devices with Blake Design Improves Arch Structure in Developing Children


·        39 Flat Foot Children studied by x-ray evaluation over 6 years old (average age 10.3, range 6 to 14 years old) for a 2 year period to see if the arch developed with Blake Inverted Orthotic Design

·        Blake Inverted Orthotic Design is recognized worldwide as providing the most medial arch support


Orthotic Device cross section standard heel cup (right) and Inverted Technique (left)

Orthotic devices resting under Inverted molds (typically one foot more inverted than the other

Standard right arch and Inverted left arch
·        One study showed that if children were to spontaneously reduce their flat feet (grow out of it) it would be before 6 years old. Dr Ron Valmassy says it is predictable at any age, but 8 years old is the gold standard of knowing if they will grow out of it.
·        4 radiological angles (which measure arch collapse in the sagittal and transverse planes) and one standing angle (measuring frontal plane) were measured at the start of the study, 12-18 months into the study, and at 24 months.
·        Subjects were required to wear orthotic devices for 8 hours per day minimal
·        Exact Rx writing was used to individualize the custom orthotic devices based on the RCSP (Resting Calcaneal Stance Position).


This measurement, called the resting calcaneal stance position, changed from 8.0 everted to 1.9 everted with orthotic wear over the 2 years, and measures the frontal or coronal plane component. The ideal is 0 degrees or heel vertical measured exactly with a goniometer.


Inverted RCSP with goniometer.jpg

Here the exact angle is being measured with a goniometer.

·        2 of the 5 angles showed significant improvement, 2 of the angles showed improvement, and one was unchanged (the least predictive one generally)
·        Background Info: Blake Inverted Orthotic developed here at Center for Sports Medicine throughout the 1980’s. Dr Blake has lectured nationally and internationally about the technique. At one point, 17% of all custom made orthotic devices in Australia were this technique.
·        More Background: Bias of Pediatricians and Orthopedic Surgeons is that all children with flat feet will outgrow this, or at least there is no predictability in selecting children for orthotic devices. Dr Ron Valmassy developed the criteria in the late 1970s for predicting which children will not outgrow their flatfeet and also has lectured extensively.
·        Flatfeet: flexible and rigid. Flexible is the hardest to correct in adults and these were the ones chosen for the study (typically more ligamentous laxity than a rigid flatfoot). Flexible flat foot is much more common to see however in children, and can develop into rigid flat feet after the age of 22 when the adult ligament and bone structure is fully developed.


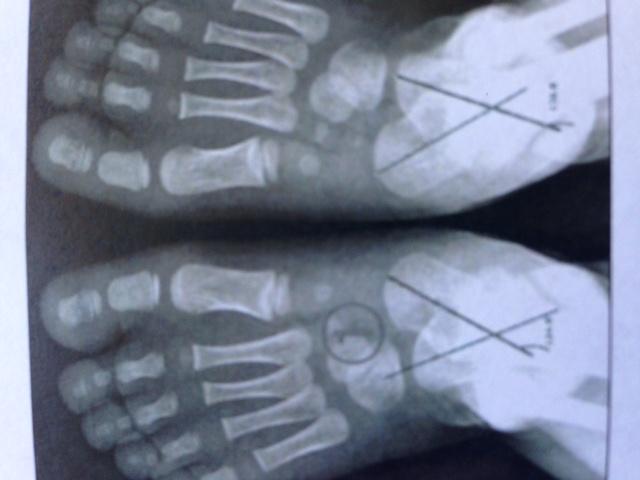
AP TCA is decreased as the arch gets better and the foot less splayed out (Angle 1)

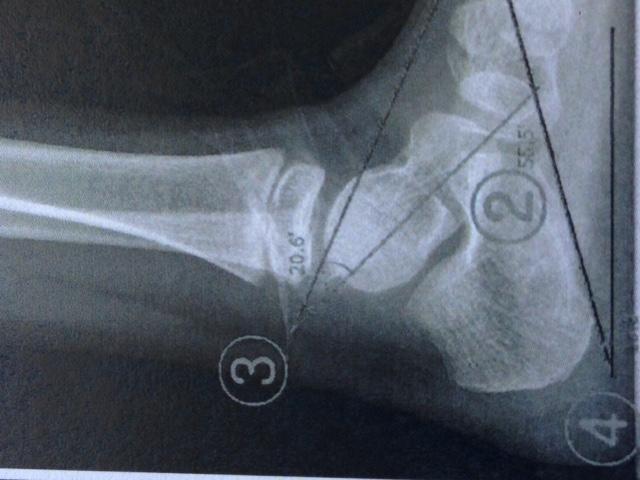
Lateral TCA should get less as the arch improves (Angle 2)
Lateral TMA should get less as the arch improves (Angle 3)
CP should get greater as the arch improves (Angle 4)

·        RCSP changes  8.0 to 2.6 to 1.9  (less is good)
AP View TC Angle 38.4 to 38.1 to 29.6 (less is good) Angle 1 above
Lateral View TC Angle 47.3 to 49.8 to 47.3 (less is good) Angle 2 above
Lateral TM Angle 17.7 to 18.2 to 10.3 (less is good) Angle 3 above
CP Angle 11.6 to 14.7 to 16.0  (more is good)  Angle 4 above

Dr Blake’s comments:
·        Article used the Blake Design to customize the orthotic prescription typically not seen in foot orthotic studies (allowing the 5 to 1 rule of cast correction to heel eversion to create an equal and opposite force to control pronation)
·        The calcaneus is the best guide since it can be accurately measured in the sagittal and transverse planes (by the calcaneal pitch) and the frontal plane (by the RCSP) since it is trapped against the ground. The talus is notoriously a poor guide since it is influenced by the foot and ankle (and ankle positioning is not standard with these x-rays). 

Sunday, June 14, 2015

Running Shoe Lecture: Power Point Presentation

This is the second lecture I will give at our State Podiatry Meeting in several weeks. This again emphasizes the practical. 

https://drive.google.com/file/d/0BwmEZgwJ3YN7ZFVwYmJmZXRLSnM/view?usp=sharing

Saturday, June 13, 2015

Walking vs Running Mechanics: Lecture in PowerPoint

This power point presentation is for my State Meeting in several weeks. So, it is written for a podiatrist of various degrees of knowledge on the subject, and geared for practical advice.

https://drive.google.com/file/d/0BwmEZgwJ3YN7TUl4Tmx0RGlzX2c/view?usp=sharing

Wednesday, June 3, 2015

OESH Shoes: Unique Shoe to Know About for Wide Forefeet

http://oeshshoes.com/

All of these OESH shoes are zero drop (no heel lift), and very straight lasted with wide forefeet). This is unique, and many patients may fit into when the forefoot width of standard shoes is too narrow.

Tuesday, June 2, 2015

Help for bunions and hammertoes: Correct Toes

I have been looking for a product like Yoga Toes, that will be help to hammertoe and bunion patients, and that can be worn to walk in some shoes. One of my patients is wearing Correct Toes while walking in Keen (extra wide) athletic shoes. I hope it helps some of you. Rich

Monday, June 1, 2015

Arch Taping: Support the Foot Brand Excellent


The video above is a small introduction to a great taping technique for foot stability. So many foot problems are improved with taping, and this is one of the best new techniques I have seen in years. I first was introduced to the technique in July 2014. I have used the foot strapping in now 100 or so individuals with very good results. It runs about a dollar per day, and lasts 4 days or so. It survives showers and soaking, but not swimming pools. Go to their website. It is super easy to apply. I will try to make my own video soon. They sell in groups of 5, so you do not have to make too much of a committment before purchasing. Good Luck

Saturday, May 16, 2015

6PM.com place for athletic shoes discounted

http://www.6pm.com/

One of my patients told me that this was a wonderful place to get athletic shoes at a discount. Please check it out. It also has everything else, perhaps even the kitchen sink.


Foot Nerve Pain: You Tube Video Comment Reply

Hi Dr Blake, I have excruciating pain in between the 1st & 2nd metatarsal. (4 years ongoing). It only happens when I walk for long, try to run, carry heavy items or wear tight shoes. MRI scans showed nothing, XRays showed nothing. Could it be a neuroma? Massaging it helps alot. The cold also aggravates the pain. Anti inflammatory meds help as well as lyrica for nerves. My guess it is a pinched nerve or a neuroma.

Dr Blake's comment:
With the negative scan, this is typically an L4/L5 nerve root irriation or double crush syndrome. Neuromas are rare in this area. Look into neural flossing/gliding and topical NeuroEze. Have the nerves evaluated by a neurologist or physiatrist for radiculopathy. Definitely try to manipulate the weight bearing with Hapad Longitudinal Arch Pads and try restricting toe motion with toe separators, Budin Splints, spica taping. Ice Pack for 10 minutes twice daily for the next month to see if this is helpful. Hope this helps.

Saturday, May 9, 2015

Big Toe Joint Pain from Running: Email Advice

Hello Dr.,

I do not know if this email is still active, but I wonder if you could give me some advice.  I am a 27 year old active male who, for the last 7-8 years has had big toe pain in my left foot.  It seems to exacerbate on exercise and calm down when I rest it.  It doesn't seem to be getting worse, although it does tend to be quite tender after running.  I have no bone spurs that I can feel, and retain the same ROM as the other foot.  I had x-Rays about 7 years ago when I noticed it and the podiatrist suggested the usual hard sole shoes and orthotics, which I didn't follow through with.  Should I be treating this like a sore joint and avoiding exacerbating activities, or should I be looking into surgery?  If it is the latter, which surgery might retain maximal functionality of the toe ultimately?  I appreciate your time and your response.

Dr Blake's response:
     Thank you so very much for your email. In a situation like this, you have plenty of time to find 3-5 things that help you de-stress the joint and perhaps slow down the joint breakdown. You are way too young to do joint surgery, and there is no surgery out there that makes the joint better. You can make a toe straighter, you can remove bone spurs that get in the way of motion, you can fix or remove broken bones, but unless we had more info, you can not make the joint better by cleaning it out. 
     What typically makes big toe joint better are biomechanical changes (shoes, pads, orthotics, activity modifications), anti-inflammatory measures (icing, PT, contrast bathing, topical and oral meds), immobilization measures (cross training, plates, spica taping, stiff sole shoes, removable boots) and getting further information (xrays, MRIs, bone scans, CT scans).
     My goal for you would be to try one thing a month for the next 7 months (like icing for 10 minutes twice a day). Definitely use the KISS principle: Keep It Simple Stupid by using the least invasive things first. Find 3-5 modalities that help somewhat (10-20%) and make yourself a cocktail for less pain. Hope this works for you. Rich

Tuesday, May 5, 2015

If you think I know what I am doing, read this!! At least I have great patients!!

Hello my most exceptionally wonderful and PATIENT Dr. Blake.  It was so nice to see you again. You always make me feel like we are in this together and that I'm not being left hanging out on a limb all alone!  The last adjustment we made did not seem to help much with off loading the lateral column. I noticed almost immediately that I had lost some of that wonderful support I had been enjoying and am pronating more than I was.  I have had to add arch to both orthotics. Taking the wedge off the topcover helped tremendously but I am still having numb toes and soreness along the lateral side.  I tried the met pads in every possible way and even bought some of the blue hard ones thinking they would be better.  They just seem to press even harder on the nerve.  I knew I had neuromas but apparently they have been dormant for years.  Your website said to try different shoe gear so I bought three different pair from your list and have had no better luck with any of them.  I know you said the fifth mets were dropped so could that be the issue?  You are so knowledgeable so I will not even try to interject my thoughts here.  I really don't want these numb toes to become a permanent fixture but don't know what else to try.  Sorry to be such a pain.
I await your suggestions but amputations and lobotomies are not possible.😁

Thursday, April 30, 2015

World Golf Championships at Harding Golf Course, San Francisco

4-30-15

Today I did some First Aid at the World Golf Championships in San Francisco at our beloved Harding Golf Course. As a member of the medical team, I treated various foot and ankle injuries, only on the spectators. I will be back for Saturday May 2nd for the Semi-Final round. I thought some photos could give a taste of my day. 


Dignity Health is the wonderful Hospital Chain I work for.


The tourney was largely sponsored by Cadillac. This is a little view of how the 5 days of Golf would go.

Harding Golf Course is next to Lake Merced, right on the San Andreas Fault line


Here is our medical team, minus me taking the photo, with EMTs, RNs, MDs, and cordinators.

Dr Richard Naidus, my collegue for 35 years, and one of the San Francisco Giants physicians and myself. It is important to note that I was standing on the down part of the slope. 

Here with my walkie talkie I am ready to go mobile. No blister is safe with me on the prowl. 


64 of the top Golfers in the World are here in San Francisco. Tiger Woods did not make the cut. Here is a few shots of Harris English.


My friend Patte McDowell will be happy I captured a shot of Graeme McDowell 

Sunday, April 26, 2015

A Discussion on Running, Running Shoes, and Walking


     I am preparing a lecture for our state podiatry meeting at the end of June this year. It is entitled Running vs Walking: How are they different? As I prepare for the talk, I find this blog and any comment you may have will be very helpful. There are many theories out there on what the right running form is, or the right running shoe, or is running better than walking, etc etc. I will begin to analyze in this blog post that I will update constantly over the next 2 months. It will be a work in progress to fine tune my thoughts. 

     So, what does a podiatrist want to accomplish with more information about running, walking, and running shoes. Probably most of all to help patients avoid injury or speed up the rehabilitation of an injury in progress. And, this information can be imparted to the athlete on how to make running much more enjoyable and actually better in the long run.

     Most know that running and walking provide similar health benefits (better cardiovascular, less diabetes, less blood pressure and cholesterol), you just have to do 2.5 times the amount of walking than running to accomplish that feat. Thus, one hour of running produces the same amount of benefit to the body as 2.5 hours of walking. A benefit of running however is that it releases peptide YY to reduce appetite so runners are leaner for sure. Walking definitely has less injuries and less wear and tear on the body, with studies showing 40-80% of all runners getting injured every year. Real Age Benefits of walking: 10,000 steps per day makes men 4.1 years younger and women 4.6 years younger.

     Where does a podiatrist fit in? We must be able to help patients with injury treatment that includes: shoe recommendations, orthotic devices when needed, running style changes, training guidelines, stretching and strengthening help, and advice on what makes sense and what does not.
I think that will be be part of this lecture recognizing fads, shams, great ideas well tested, and you definitely have to keep an open mind.


     Most will agree that there are aspects of running form that create smoothness, efficiency, less injuries, and more power. The image above clearly shows some of them: upright posture, arm swing compact, slight forward lean of the trunk, foot land under or just in front of the body.

In this photo, the forward body lean is exagerated.


Here the runners going stride for stride appear to be overstriding, a cause of many injuries, where there foot strike is too far in front of their bodies. The impact shock needing to be absorbed by the muscles and skeleton, and the deceleration needing to be stabilized by the muscles, makes overstriding very energy inefficient.

     If you talk to college track and cross country coaches, one of the key changes they have to make in a freshman runner is to run with a greater stride rate (or cadence) and much less stride length. You can run faster in two ways: longer strides or faster cadence. As the runners above show, the longer their strides the more impact shock to the knees and hips. Since typically overstriding is associated with a heel strike pattern, it gives heel strikers a bad name. You can over stride with a heel strike form, a midfoot strike form, or even a forefoot strike form. 

An exagerated heel strike from overstriding

His overstriding will produce a midfoot strike. See how far infront of his body his heel is, classic sign of overstriding. This produces greater up and down motion (not efficient since we want forward motion only) requiring more effort from the legs to cushion the fall). 


     One of the tricks we have taught our runners is to keep the cadence at 170-180 steps per minute, overstriders run at 150-160 steps per minute. I have a metrenome on my iPhone that I can set for this to practice the step rate. Remember 2 strides equal one step (A step is the time you put one foot down until you put that same foot down again). A stride length is from heel contact of one foot to heel contact of the other foot.  When you are overstriding, you are going slower than this, using greater stride lengths to achieve faster speeds. Remember, you can have an efficient 170-180 cadence at any speed, but this cadence is the most efficient.

     There are a few tricks out there for better running: cadence of 170-180, lighter shoes, lower heel height, slight forward lean with pelvic/core training.

   
To be constantly continued.....


Sunday, April 19, 2015

Sesamoid Injury: Email Advice


Dear Dr. Blake,

     Firstly thank you for all of your support you give to this issue. When researching my condition I have found your website to be of great value. Mostly because I can relate to much to all of the other people dealing with such a tough issue.

     I was diagnosed with sesamoiditis about 8 months ago. I have tried every treatment I know of besides acupuncture, which I am putting my hopes in now as I have an appointment tuesday.

     I have a
bipartite sesamoid in my right foot. I had a hot spot in the bone scan followed by a CAT scan. Two doctors have agreed that from the scan that there is no fracture.
Dr Blake's comment: I always treat a positive bone scan as a stress fracture, since you have the treat the most serious problem, and CT scans and x-rays will not show the fracture itself (even when the bone is broken). 

    I have been in a boot for two months, tried rigorous icing and heat daily, anti-inflammatories (which I am not off for being on too long, plus they didn’t seem to do anything), dancer pads - minimal help, off the shelf and custom orthotics - little help there. Two cortisone shots - the second one worked for about 7 weeks. Then slowly back to square one.
Dr Blake's comment: The thing with orthotics and dancer's pads is that they have to shift the weight to the middle of your foot and off the sesamoid. If not, get them adjusted. Cortisone is to be shied away from because of the possibility that this is a stress fracture and cortisone can slow down the healing process. 

    I was a sub 3 hour marathoner and used to run ultra marathons and climb mountains for fun, so being stuck swimming laps is often a tough pill to swallow. Besides swimming and low impact activities and the once every two months a short run just keep sane- no long walks, no hiking, no mountaineering, very few casual runs. My podiatrist has stated that he is not convinced surgery is worth it yet and it may just heal.
Dr Blake's comment: I am glad your podiatrist is sane. At some point, get an MRI to see how much bone edema still exists in the sesamoid. If positive, then you also should be on a bone stimulator. It is great you are cross training and trying to create a pain free environment. 

    When discussing the idea he has brought up a partial sesamoidectomy stating that with my bipartite the offending bone is slightly smaller, so he should be able to take out half, hopefully leaving me with full function. He also stated under the preface “if you’re game” It would be an experiment, but trying a bone graft to join the two parts, but he wasn’t sure if this had been done or where he would take the bone from to graft it - does this sound feasible? Has anyone else done this?
Dr Blake's comment: If 6 months from now, only one of the two sesamoid pieces remained hot on MRI and you were still struggling, I would entertain a partial sesamoidectomy, but only then. Never heard about bone grafts across the fracture site. 

    I am also seeking a third opinion outside of the clinic which I go to. Is there a sesamoid specialist in the greater pacific northwest who has experience in this issue? It seems very difficult to find a podiatrist who has a great deal with sesamoid issues not that I don’t think they are out there, its just how to find them.
Dr Blake's comment: I typically recommend Dr Richard Bouche in the Seattle area, he is very smart and deals with athletes all the time. 

 My last question is the current surgeon I have been seeing has performed 50 or so sesamoidectomies, I have no idea if this is an adequate amount of experience? Is 50 a lot or a little...
Dr Blake's comment: After 3 or so you have good adequate experience, after that it helps fine tune the thought process on when to operate, and what to do post operatively. I hope this helps. 
If you’ve read this far, thank you for your time, any advice you can offer would be greatly appreciated. I would give anything to have my life back.

Thank you,

Saturday, April 18, 2015

Peroneal Tendon Injury: Email Advice

Dear Dr. Blake,
I am in my late 50s and fractured my os peroneum bone into several pieces along with tearing my peroneus brevis and longus tendons making a sharp turn, walking in my office.  I did not twist my ankle...I was just walking.  I would greatly appreciate any advice you have for me.
I stupidly delayed treatment for 5 months, but have now completed 10 weeks in a short CAM walker including a) 10 weeks of wrapping sponge and Elastikon tape around my foot, in front of the ankle (yet covering the os peroneum) and b) 7 weeks of using the Exogen bone stimulator twice daily.  The new Xray shows slight new bone being deposited in the area.  I am just starting the process of gentle stretching and weaning out of the boot.  Your website has really helped me (and others I am sure) now understand good pain versus bad pain, and how to wean into a shoe.
Dr Blake's comment: Your injury does not make sense. How could you fracture a bone and tear two tendons without a significant fall/sprain? "Something is rotten in Denmark" borrowing from Shakespeare. But you did injure something, and did not get it treated for 5 months, so you placed yourself into the Immobilization Phase. I would only be convinced of a os peroneum injury with a positive bone scan, or bone edema on MRI. Please email me with other info you have. 
Thank goodness I no longer have the os peroneum syndrome sensation of stepping on sharp rocks.  If you have time, I would appreciate your answers and any treatment suggestions that you have for me:
1.      Have you successfully treated os peroneum fractures?
Dr Blake's comment: Our surgeons have had to remove several, and several just stopped hurting with orthotics, etc. I have seen so few that I do not have a great understanding. Several I thought were not injured, it was just the inflammation from the tendon injury that made the bone look inflamed. You did the right thing getting the bone stim.
2.      Do you think that I should continue to tape my foot?  If so, what tape brand and where would you recommend that I apply it?  The recommended Elastikon tape around my foot in front of my ankle in the shoe is bulky, even with the new extra wide sneaker with a wide base.
Dr Blake's comment: I love this tape you get at www.supportthefoot.com. Get the small size. 
3.      I have a naturally wide foot.  I feel pressure from the tied sneaker being pulled over the os peroneum area.  Should I cut a hole in the sneaker so that it doesn’t rub that area?
Dr Blake's comment: I am afraid that that would lead to some instability. Get some 1/4" adhesive felt from www.mooremedical.com and place on your foot in areas that take the pressure off the sore area. 
4.      My podiatrist wants to firmly press along the tendon and broken bone every time I see him.  I am worried about aggravating or slowing down the healing process.  Should I be?
Dr Blake's comment: No, that does not come close to weight bearing stress. However, soreness from this problem will remain for up to 1 year longer than the injury, as the healing continues. So, palpable soreness is a poor way of judging healing. Gradual improvement in function, or lack of improvement, is a better way. 
5.      Does the bone stimulator help?  Can it hurt if I use it too long?
Dr Blake's comment: Unsure if it helps, since I am not sure what you have, but if will do no harm. 
6.      When will it be OK for me to wear 1” wedge shoes again?  Before I went into the CAM walker, I found that a slight wedge shoe was actually more comfortable because it shifted the weight off of that area of my foot.
Dr Blake's comment: You are gradually moving from the Immobilization Phase, through the ReStrengthening Phase, and into the Recovery to Activity Phase. You said that you tore some tendons, are you doing something to get them strong? MRIs typically show peroneal tendon problems when they do not exist. I would need more info on those tendons. You should be doing peroneal tendon strengthening exercises, and gradually introducing various shoes to see what works (start with one hour at a time). You really do not know how healed you are right now. Go easy. 
7.      Other suggestions?
Dr Blake's comment: I love orthotics for this, but the doc/therapist/pedorthist has to know about stabilizing that half of your foot (lateral one half). See my blog posts on supination correction with orthotics to give you some idea. Definitely, continue icing and contrast bathing daily to control inflammation and increase healing with swelling control. Good luck!!
Dr. Blake, thank you for taking the time to get back to me.
Gratefully,

And the patient's response:

Dear Dr. Blake,

Thank you for all of your good advice and especially for the reminder to go easy. I needed that.

By way of background, I should have mentioned that an MRI confirmed the X-ray finding of a fractured  os peroneum which is now in many fragments.  For comparative purposes, an X-ray of my good foot showed an intact os peroneum.  It was a freak injury where I was walking quickly and took a quick turn.  It felt like someone hit me in the foot with a bat.  Two radiologists independently confirmed the fragmented os peroneum, severe partial tears of the perroneal brevis and longus tendons and that the distal peroneum tendon appears thinned. Besides intense pain flexing my foot away from my body, I had the sensation of stepping on sharp stones with every step and weakness/the inability to lift my heel and go up on my toes on the one bad foot.

You have me thinking now that there is something rotten in Denmark.  It has been about 8 years since my last bone scan, and maybe it is time for another.  I have been practicing yoga barefoot for about 10 years.  Would flexing my foot at 45 degrees in certain yoga lunges  or downward dog poses put added strain on the tendons simply because I have an os peroneum bone?  What causes a tendon to thin?  I sure welcome any insight you have to help prevent this from happening again.

Still grateful,

Dr Blake's comment: 
     Thank you for the response and confirmation that we are dealing with an Os Peroneum Fracture. The bone is so buried in your foot, I have a hard time understanding how it breaks in the first place without a history of a fall. A bone density screen is great. Again, the peroneals get thinned and look bad on most MRIs even when they do not hurt (more mystery). How is the tendon function? Are you strengthening the peroneus longus and brevis? Rich

Post Cortisone Shot in CRPS patient: Email Correspondance


Dr Blake's comment: This patient developed CRPS after a cortisone injection for a neuroma. She has had quite a journey with many ups and downs. Calmare Pain Therapy has been crucial in her treatment to quiet the nervous system. This email was followup to a cortisone shot I just gave her to shrink down a Morton's Neuroma left foot now that her symptoms are not systemic, but more local. We both realize that the neuroma was producing a chronic amount of neural tension in her body, and needed to be somehow addressed. 

Dear Dr Blake: 
It went very well! The pain stayed away all that day till 5 pm (shot given around 10 am was a mixture of local anesthetic 0.5% Sensorcaine and long acting Cortisone Kenalog 10).

Since then I have had some minor flare, but less flare than with any other shot in the past (including pre-CRPS shots)! Only a few cruel "zings" up the leg, and locally increased burning in a 2-inch diameter around the injection site, and also strong burning in 3rd and 4th toes. But completely tolerable.

I think the flare is calming down today and by this weekend I'll be completely in the "benefit" stage of it. I hope it allows me to walk longer/farther and increases my standing tolerance too.

From my lay-person experience, I recommend the combo of Synera patch 30 minutes before injection (placed on the top and bottom of her foot)and a single 5 mg dose of Valium for anyone who has CRPS or you think is at risk of CRPS—just to minimize the sympathetic activation around the experience. Maybe add 10 mg of Nortriptyline the night before and the night after, for even more suppression of nerve pain, so that the CRPS cycle doesn't get started.

Thank you so much for all your care and expertise. You are the only person I would ever let inject my foot!

Would you tell me what drugs/dose were in my shot? (see above--1 ml of each). I am considering an occipital nerve root block next week, and the doctor wants to know how much cortisone I got this week to make sure it's not too much in my body (even though in a totally different place).

I'll report in next week to let you know the longer-term benefits of the shot.

With much gratitude,

Further patient comment:

     Hi Dr. Blake,

I am doing well now.

It took about two and a half weeks for the flare from the shot to calm down! Longer than I expected. But the amplitude of the flare was not bad, so I was not in cruel agony like in past years. 

So now I will see if I can up my walking tolerance even more, and/or begin to wear a shoe. The Oesh brand shoes do seem really good for neuromas, you might want to check them out. But my foot is still hypersensitive enough that I dread wearing any shoe. Still, I know it is not ideal mechanics to walk in flip flops—there is some constant toe flexion to hold the shoe on—so it would be better if I could wear a closed shoe, or at least a sandal with a strap around the heel, if I could find one with a comfortably cushioned footbed.

I just met with one of the directors of the pain dept at Kaiser to see if I could get them to buy a Scrambler machine, but there are all the same obstacles there. I'll let you know if I make any progress on that front.

Hope you are well!